006
This case report describes an uncommon but serious complication related to endotracheal tube (ET) cutting while in situ.
A 46-year-old male was intubated with an uncut size 9 endotracheal tube and ventilated in the intensive care unit (ITU) due to respiratory failure as a result of community acquired pneumonia. Twenty four hours after intubation the ET needed to be cut in order to facilitate lung suctioning and physiotherapy, this was performed by senior ITU doctor and documented as straightforward procedure. Following this, the patient oxygen requirement has increased with the ventilator alarming air trapping and increasing end tidal carbon dioxide. Chest x-ray was performed and reported by the radiologist as left lower lobe volume loss and pleural effusion with no intrapulmonary abnormality demonstrated on the right side, multiple bilateral rib fractures noted.
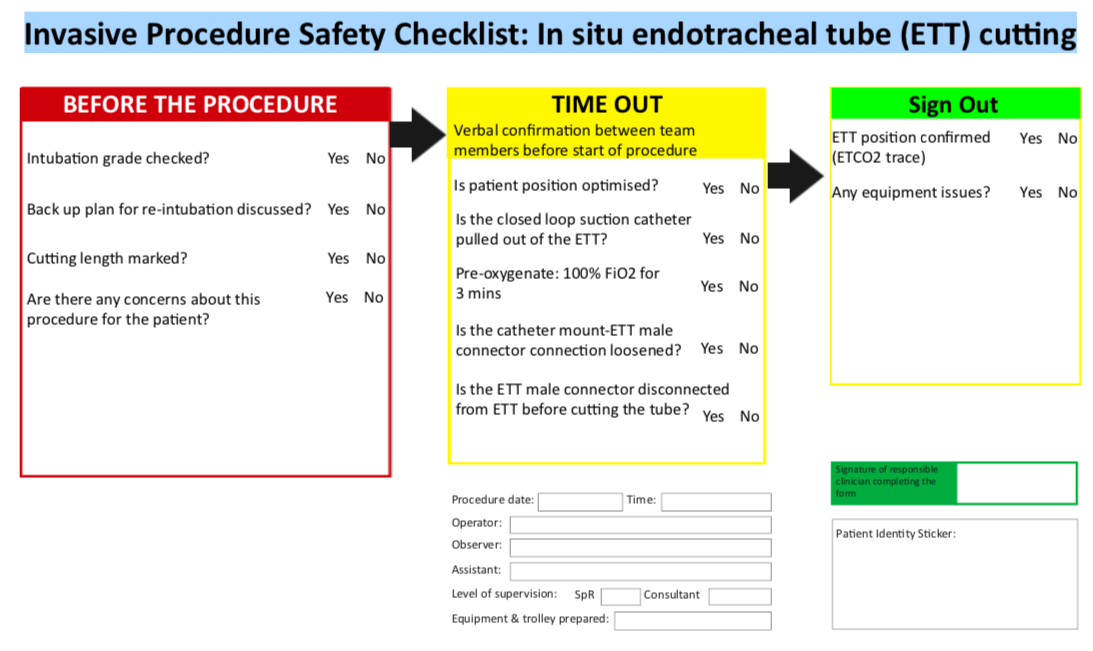
A tubular foreign body was found on routine bronchoscopy 13 hours after the ET cutting, it was lying inside the bronchus intermedius and occluding the right middle lobe. This was successfully retrieved with a grasper and found to be the distal end of closed loop suction catheter. The doctor who performed the ET cutting procedure reported the ET was cut without disconnecting the male connector and the suction catheter was not checked that it has been fully pulled out of the ET prior to cutting, this has led to cutting of the catheter tip within the ET and dislodging it into the patient airways.
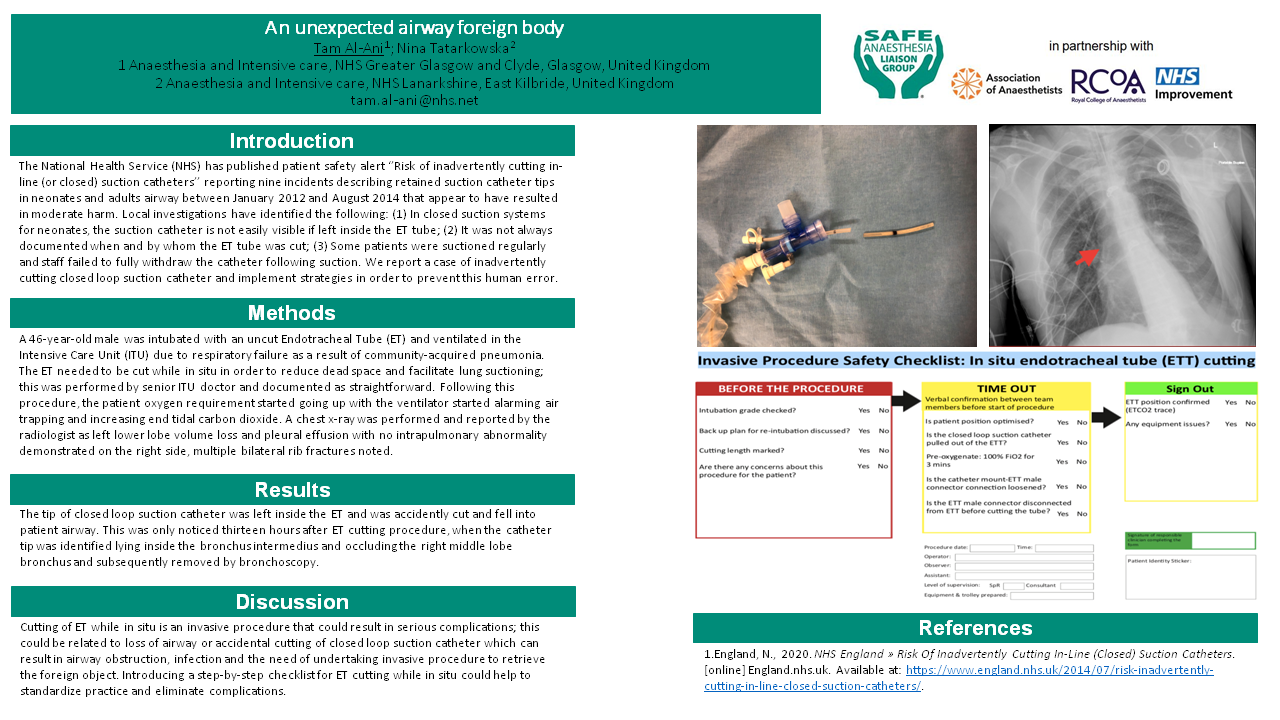
Introducing a step-by-step checklist for ET cutting while in situ (Image 1) could help to standardize practice and eliminate complications.